What Is the Child Behavior Checklist? The CBCL and Its T-Score Bands
The Child Behavior Checklist is a parent-report form that rates a child's emotional and behavioral problems against age norms as T scores. It is not an IQ test.
Dr. Russell T. WarneChief Scientist
Share
The Child Behavior Checklist is a standardized questionnaire on which a parent or caregiver rates a child's emotional, behavioral, and social problems, and the raw ratings are converted to T scores against norms for the child's age and gender. The CBCL measures reported problem behavior, so it is not an IQ test and it does not measure cognitive ability at all.
This page covers where the CBCL sits in the larger family it belongs to, where its scales came from, what the DSM-oriented scales added, how to read the T-score bands correctly, and what a clinical-range score does and does not license.
The CBCL is one form in a cross-informant system
The checklist belongs to the Achenbach System of Empirically Based Assessment, or ASEBA, which spans ages 1½ to 90 and over in translations in more than 100 languages. The system is built so that the same problems are rated by several people who see the child in different places, on forms whose scales line up with one another.
• CBCL/6-18: Completed by a parent or parent surrogate in roughly 15 minutes. It carries 20 competence items and 120 problem items, each rated 0 for not true, 1 for somewhat or sometimes true, and 2 for very true or often true, describing the child now or within the past six months.
• TRF/6-18 and YSR/11-18: The Teacher's Report Form is completed by teachers and other school staff, and the Youth Self-Report is completed by the young person. Their syndrome scales come from factor analyses coordinated across all three forms, which is what makes a side-by-side comparison meaningful.
• CBCL/1½-5 and the C-TRF: The preschool pair rates 99 problem items, with the parent form adding the Language Development Survey, a parent-report measure of expressive vocabulary against norms for ages 18 to 35 months.
• Multicultural norms: Scores can be displayed against norms for societies with relatively low, intermediate, or high problem scores, drawn for the preschool forms from more than 30,000 forms across 30 societies.
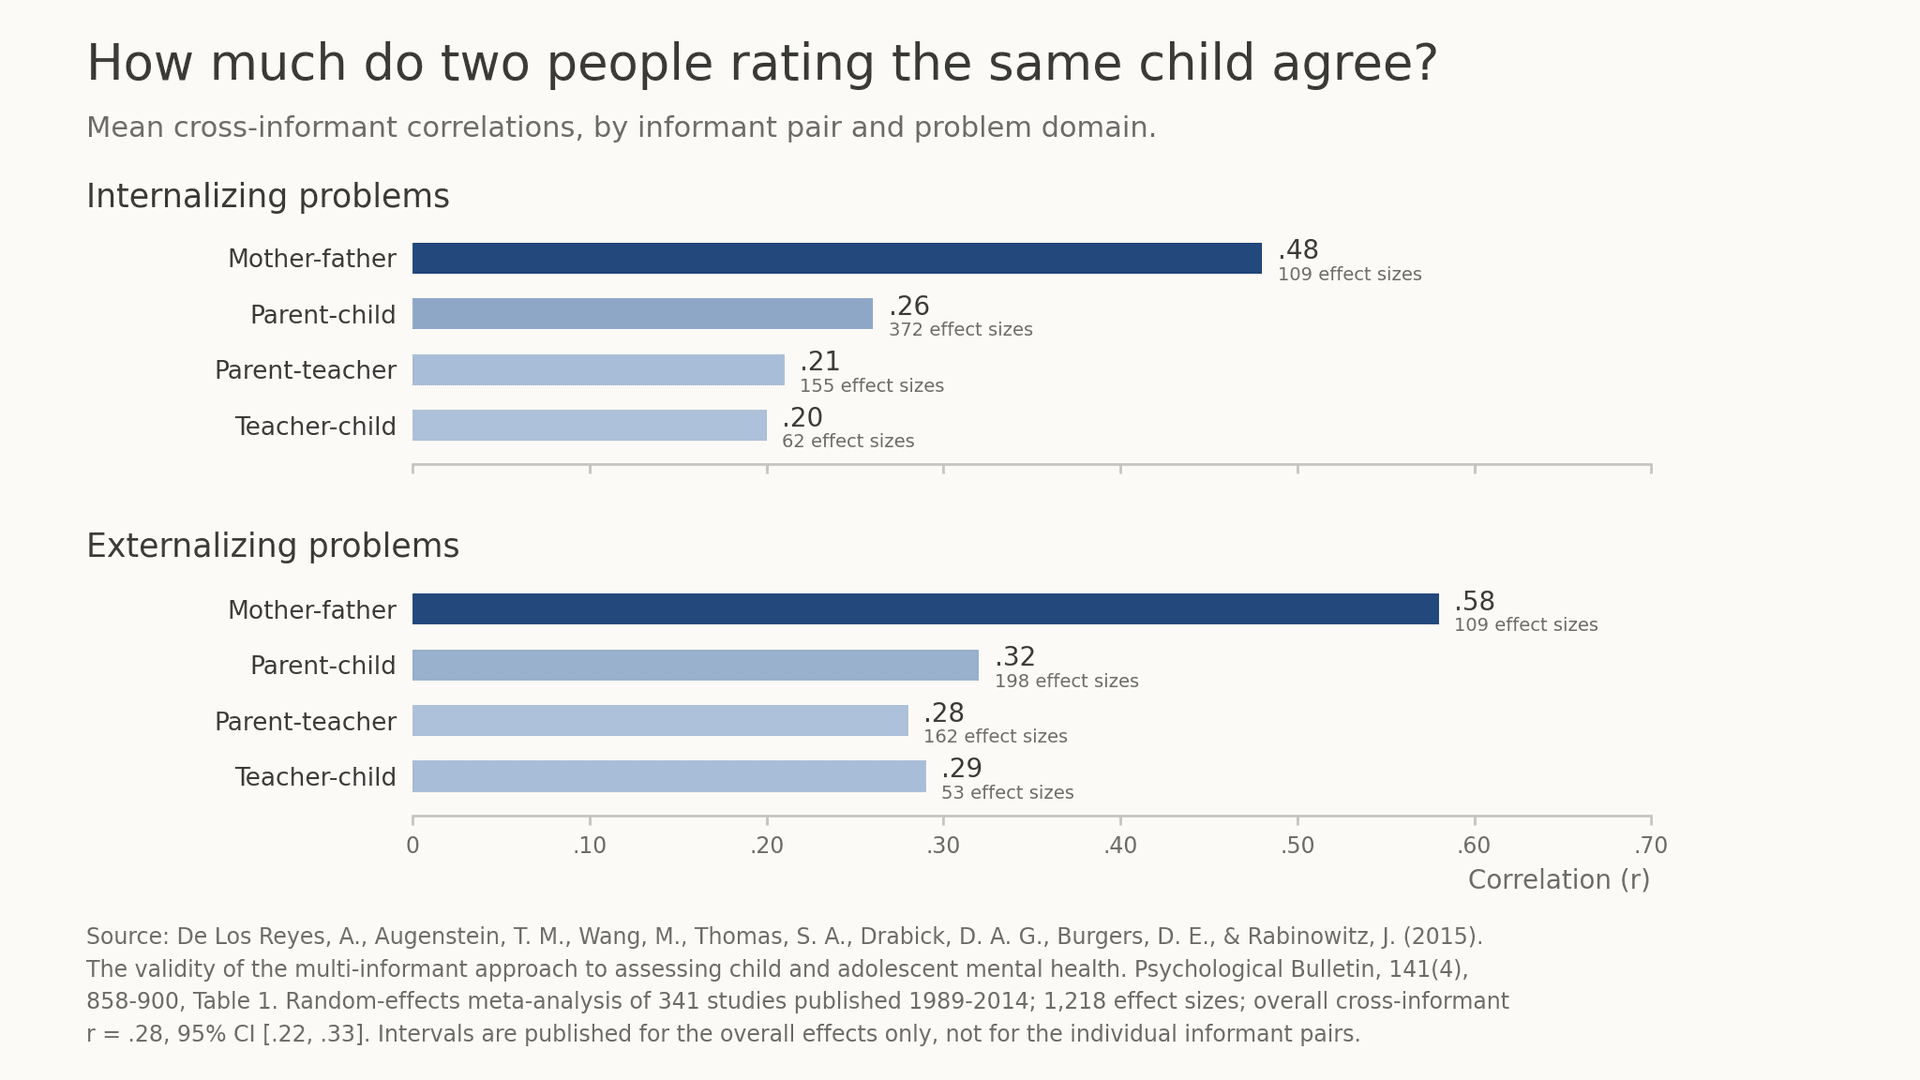
Expect the informants to disagree. A meta-analysis of 341 studies found an overall cross-informant correlation of .28, highest between two parents in the same household and lowest between a teacher and the child, and our article on adaptive behavior assessment treats that finding as the measurement problem it is.
Where the syndrome scales came from
The eight school-age syndrome scales were not copied out of a diagnostic manual. They were derived by rating large samples of children and letting multivariate analysis of the correlations show which problems travel together.
That history explains the instrument's shape. When Thomas Achenbach began this work in the 1960s, the DSM offered exactly two categories for childhood disorders, Adjustment Reaction of Childhood and Schizophrenic Reaction, Childhood Type, and his 1966 factor-analytic monograph was an attempt at a more differentiated picture than those two labels allowed.
The CBCL/6-18, TRF, and YSR are scored on Anxious/Depressed, Withdrawn/Depressed, Somatic Complaints, Social Problems, Thought Problems, Attention Problems, Rule-Breaking Behavior, and Aggressive Behavior. The first three aggregate into an Internalizing composite, the last two into an Externalizing composite, and all problem items into Total Problems. The preschool forms carry their own set.
A syndrome name labels a cluster of co-occurring items, a weaker claim than a diagnosis. "Attention Problems" names a factor that emerged from the data. It does not assert that a child scoring high on it has attention-deficit/hyperactivity disorder.
The DSM-oriented scales were added later and built differently
Because clinicians and payers work in diagnostic categories, the 2001 revision added a second family of scales, built by a different method. Experts from many cultures rated each item for consistency with DSM categories, and items that enough of them judged very consistent with a category were grouped into a scale for it. The exercise was repeated for DSM-5 with experts from 30 societies, which is where the preschool Autism Spectrum Problems scale and the revised Anxiety Problems and Somatic Problems scales came from. The six scored from all three school-age forms are Depressive Problems, Anxiety Problems, Somatic Problems, Attention Deficit/Hyperactivity Problems, Oppositional Defiant Problems, and Conduct Problems, all drawn from the same item pool as the syndromes.
Their diagnostic labels are easy to over-read. In a referred sample of 360 Italian children and adolescents, Bellina and colleagues found the DSM-oriented scales were more specific than the syndrome scales yet more weakly associated with actual DSM-IV diagnoses, and the associations crossed categories: a clinical score on Oppositional Defiant Problems predicted generalised anxiety disorder as well as oppositional defiant disorder.
Reading the T-score bands, where the cut points differ
Every CBCL scale is reported as a T score with a mean of 50 and a standard deviation of 10 in the normative sample, separately by age band and gender. The 2001 school-age norms come from a national survey run between February 1999 and January 2000, with a non-referred sample of 1,753 children from 40 states. Rating-scale T scores are a different metric from an IQ score, and our article on the Conners test works through how that metric behaves.
The interpretive bands are where readers most often go wrong, because the narrow and broad scales use different lines.
• Syndrome scales and DSM-oriented scales: Below 65 is the normal range. T scores of 65 to 69, the 93rd to 97th percentile, are the borderline clinical range. T scores of 70 and above are the clinical range.
• Internalizing, Externalizing, and Total Problems: Below 60 is the normal range. T scores of 60 to 63, the 84th to 90th percentile, are the borderline clinical range. Scores above 63 are the clinical range.
• Why the lines differ: The broadband composites pool far more items than any single syndrome, so they are more reliable and a smaller deviation is already interpretable. Reading a syndrome scale against the lower line manufactures concerns the norms do not support.
• The floor is real: No T score below 50 is generated for the narrow-band syndrome scales, so roughly half the normative sample piles up at the floor. A syndrome T score of 50 means only that reported problems were at or below the typical level, never that adjustment is unusually good.
• Competence scales run the other way: The Activities, Social, and School scales and Total Competence measure reported strengths, so low scores rather than high ones mark concern, and their cut points are reversed accordingly.
What a clinical-range score licenses, and what it does not
A clinical-range T score licenses a normed description. It says the person who filled out the form reported more of a particular kind of problem than most parents report for children of that age and gender. That is useful, and a long way short of a diagnosis.
The best current test of how far short comes from the Adolescent Brain Cognitive Development study. Chromik and Friedman compared CBCL DSM-oriented scale classifications against the K-SADS semi-structured clinical interview in 11,851 children. Specificity was high, from 92.47% to 97.07%. Sensitivity was the problem: it ranged from 10.36% to 75.00%, with only two scales above 50%, positive predictive values ran from 0.71% to 48.20%, and areas under the curve from 0.55 to 0.84. Their conclusion was that the scales "showed poor concurrent validity with a gold standard clinical interview" and that caution is warranted "due to the high rates of false negatives."
So a clinical-range score is a reasonable trigger for a closer look and a reasonable baseline for tracking change. A score in the normal range is weak evidence that nothing is wrong, since most children who met interview criteria in that sample were never flagged.
Two further boundaries are worth stating plainly. The CBCL describes behavior as reported, so it cannot say why the behavior is happening, and a high Attention Problems score is equally consistent with anxiety, a sleep disorder, a reading difficulty, or a classroom mismatch. The form also contains no ability items of any kind: no vocabulary, no reasoning, no working memory, no processing speed. A cognitive score has to come from a cognitive test. For how a different publisher handled the same rating-scale problem, see our guide to the BASC-3.
Frequently asked questions
Is the Child Behavior Checklist an IQ test?
No. The CBCL asks a caregiver to rate problem behaviors and competencies, and it contains no items that measure reasoning, knowledge, memory, or speed. Its T scores and an IQ score are on different metrics and describe different things.
What is a high score on the CBCL?
On a syndrome or DSM-oriented scale, 65 to 69 is borderline clinical and 70 or above is clinical. On the broadband composites the lines sit lower, at 60 to 63 and above 63.
Who can fill out and interpret a CBCL?
Anyone with roughly fifth-grade reading skills can complete the parent form, and ASEBA states that no special qualifications are needed to administer it. Interpretation is different: the publisher expects graduate training at least to the master's level plus supervised experience.
Can the CBCL diagnose ADHD or autism?
No. It can flag a pattern worth investigating, and in a sample of 11,851 children the DSM-oriented scales missed a large share of youths who met criteria on a structured interview. A diagnosis requires a clinician working from DSM-5-TR criteria and more than one source of information.
How does the CBCL differ from the TRF and the YSR?
They address the same measurement problem to different informants, with scales built to line up across forms. The CBCL is the parent version, the TRF is for teachers and school staff, and the YSR is completed by young people aged 11 to 18.
The takeaway
The Child Behavior Checklist is a normed, parent-reported description of a child's problems, derived from factor analysis of what large samples of raters actually report rather than from a committee's diagnostic categories. Reading it correctly means using the right band, 65 and 70 on the syndrome scales against 60 and 63 on the broadband composites, and drawing no inference at all from a syndrome T score sitting on the floor of 50. It also means treating a clinical-range score as a question. The ABCD study put sensitivity for the DSM-oriented scales as low as 10% against a structured interview, the clearest available evidence that a rating scale opens an evaluation rather than closing one. None of it measures ability, and if you want a cognitive number alongside a behavior profile, you can take an online IQ test built by psychometricians and hand the report to the clinician doing the diagnostic work.
References
1. Achenbach, T. M., & Rescorla, L. A. (2001). Manual for the ASEBA school-age forms & profiles. University of Vermont, Research Center for Children, Youth, & Families. aseba.org
2. Achenbach, T. M., & Rescorla, L. A. (2000). Manual for the ASEBA preschool forms & profiles. University of Vermont, Research Center for Children, Youth, & Families. aseba.org
3. Achenbach, T. M. (1966). The classification of children's psychiatric symptoms: A factor-analytic study. Psychological Monographs: General and Applied, 80(7), 1-37. doi.org
4. Achenbach, T. M., Dumenci, L., & Rescorla, L. A. (2003). DSM-oriented and empirically based approaches to constructing scales from the same item pools. Journal of Clinical Child & Adolescent Psychology, 32(3), 328-340. doi.org
5. ASEBA. (2026). DSM-5-oriented scales. Achenbach System of Empirically Based Assessment. aseba.org
6. ASEBA. (2026). Qualifications for use. Achenbach System of Empirically Based Assessment. aseba.org
7. ASEBA. (2026). ASEBA origins. Achenbach System of Empirically Based Assessment. aseba.org
8. National Child Traumatic Stress Network. (2026). Child Behavior Checklist for ages 6-18 (CBCL/6-18). nctsn.org
9. Achenbach, T. M., McConaughy, S. H., & Howell, C. T. (1987). Child/adolescent behavioral and emotional problems: Implications of cross-informant correlations for situational specificity. Psychological Bulletin, 101(2), 213-232. doi.org
10. De Los Reyes, A., Augenstein, T. M., Wang, M., Thomas, S. A., Drabick, D. A. G., Burgers, D. E., & Rabinowitz, J. (2015). The validity of the multi-informant approach to assessing child and adolescent mental health. Psychological Bulletin, 141(4), 858-900. doi.org
11. Huang, C. (2017). Cross-informant agreement on the Child Behavior Checklist for youths: A meta-analysis. Psychological Reports, 120(6), 1096-1116. doi.org
12. Chromik, L. C., & Friedman, L. M. (2026). Concurrent validity of the CBCL DSM-oriented scales: Evidence from the ABCD study. Clinical Child Psychology and Psychiatry, 31(4), 1890-1909. doi.org
13. Bellina, M., Brambilla, P., Garzitto, M., Negri, G. A. L., Molteni, M., & Nobile, M. (2013). The ability of CBCL DSM-oriented scales to predict DSM-IV diagnoses in a referred sample of children and adolescents. European Child & Adolescent Psychiatry, 22(4), 235-246. doi.org
14. Rescorla, L., Achenbach, T., Ivanova, M. Y., Dumenci, L., Almqvist, F., Bilenberg, N., Bird, H., Chen, W., Dobrean, A., Döpfner, M., Erol, N., Fombonne, E., Fonseca, A., Frigerio, A., Grietens, H., Hannesdottir, H., Kanbayashi, Y., Lambert, M., Larsson, B., ... Verhulst, F. (2007). Behavioral and emotional problems reported by parents of children ages 6 to 16 in 31 societies. Journal of Emotional and Behavioral Disorders, 15(3), 130-142. doi.org
15. Achenbach, T. M. (2020). Bottom-up and top-down paradigms for psychopathology: A half-century odyssey. Annual Review of Clinical Psychology, 16, 1-24. doi.org
Figure by Riot IQ. Data from De Los Reyes, Augenstein, Wang, Thomas, Drabick, Burgers and Rabinowitz (2015), Psychological Bulletin 141(4), 858-900, Table 1 (doi.org/10.1037/a0038498).
Take our professional IQ test
Want to know your IQ? Try the first ever professional online IQ test.